

EMRA Antibiotic Guide

- 94.00 Reviews
- 2.4
- Downloads
- 10,000+

Our take on EMRA Antibiotic Guide from Appgk
When I need an antibiotic reference during a busy clinical shift, the main thing I want is not a long lecture. I want a focused answer that helps me frame the next question: which drug class is relevant, what kind of infection am I dealing with, and what details must I verify before acting? That is the practical promise behind EMRA Antibiotic Guide, a free medical app from Emergency Medicine Residents' Association.
My view is that its value comes from one clear capability: putting antibiotic recommendations into a format that is easier to consult on shift than a large textbook or a broad web search. It is aimed at medical users, especially people working or training in emergency medicine, rather than patients choosing treatment for themselves. Used with appropriate clinical judgment, it can serve as a compact starting point when time and attention are limited.
The app is available to an Everyone-rated audience, although the subject matter is clearly professional. It has passed the ten-thousand-install mark and carries a 2.4 average from roughly one hundred thirty ratings, alongside about ninety-four written reviews. Those figures tell me to approach it with realistic expectations: it has a defined audience and some reach, but it is not a universally polished reference that every clinician will automatically prefer.
Fast antibiotic guidance is the app’s central strength
The useful idea here is simple: instead of opening a general medical search and filtering through unrelated results, I can go directly to an antibiotic guide designed around emergency-care decisions. That narrower purpose matters. In an emergency department, the problem is often not a lack of information; it is the effort required to find the relevant information quickly while managing a patient, speaking with a colleague, and documenting the encounter.
Best Parts of EMRA Antibiotic Guide
Things to Keep in Mind About EMRA Antibiotic Guide
I would describe the app as a point-of-care reference, not as an independent prescribing system. Its recommendations should support, not replace, the local formulary, institutional protocols, microbiology advice, allergy assessment, renal or hepatic considerations, and the patient’s actual presentation. The distinction is important because a concise guide can make orientation faster while still leaving the most consequential clinical decisions with the prescriber.
The store summary presents it as an easy-to-use way to obtain ABx recommendations on shift. In practice, that means the app is most appealing when I already understand the clinical problem and need a structured reminder. It is less suitable when I am still trying to establish a diagnosis, assess severity, interpret a culture, or resolve a complicated resistance question. A quick recommendation is only as useful as the clinical framing that comes before it.
News and Features Related to EMRA Antibiotic Guide

News
YouTube Turns a Quick Video Check Into an Hour of Watching

News
BeautyPlus Makes Portrait Retouching Feel Like Your Own
News
TikTok’s Effortless Feed Makes Every Swipe Count—and Every Mistake Harder to Undo
That is also why I would not hand this app to a patient as a treatment planner. Someone without medical training could easily mistake a drug suggestion for a personal prescription. The Everyone age label describes the permitted audience for the software, not the level of expertise needed to use antibiotic advice safely.
How I would use it during a real shift
Imagine I am covering an emergency department and a patient arrives with a suspected infection. After taking the history, checking the examination findings, reviewing allergies, and deciding whether the patient is stable, I can use the guide to organize the antibiotic part of the discussion. Rather than searching the open web for a phrase such as “best antibiotic,” I would use the app as a focused reference and then compare its direction with the department’s current practice.
Don't want to read the full review?
The important workflow is not simply opening the app and copying an answer. I would first identify the likely syndrome, then check whether the patient’s circumstances change the choice, and only then use the guide to refresh my options. That order prevents the reference from driving the diagnosis. It also makes the app more useful for teaching: a trainee can explain why a recommendation fits, while the supervising clinician can challenge the assumptions behind it.
A practical tip is to treat every result as a prompt for verification. Before acting, I would confirm the patient’s allergy history rather than relying on a brief chart entry, consider recent antibiotic exposure, and check whether cultures or source control alter the plan. I would also compare the recommendation with local resistance patterns where those are available. This extra step is not a weakness of the app specifically; it is a necessary safeguard whenever a compact reference compresses a complex decision.
Screenshots
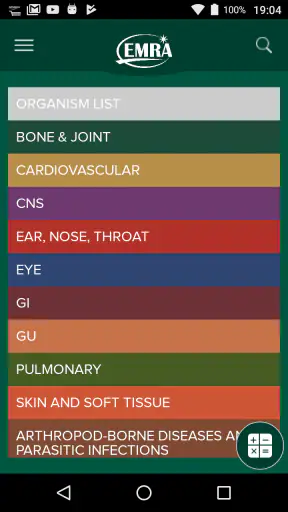
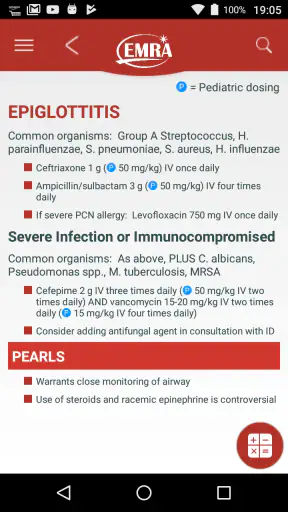
Another useful habit is to separate the initial emergency decision from the later refinement. In a seriously ill patient, immediate stabilization and timely treatment may take priority over a leisurely comparison of every option. Once the patient is safer and more information arrives, the guide can help me revisit whether the initial approach still makes sense. That makes it more valuable as a checkpoint than as a substitute for bedside reassessment.
I would also keep the app in a supporting role during handovers. A recommendation that seemed reasonable at the start of a shift may need to change after imaging, laboratory results, consultant input, or a new allergy history. Referring back to the guide can help structure the conversation, but the handover should include the reasoning and the evidence, not just the name of a medicine.
Where the focused format helps most
The best scenario is a clinician or trainee who already knows the fundamentals but wants a compact antibiotic reference close at hand. Emergency-medicine residents are a natural audience because they move between many infection presentations and may need to refresh a recommendation without carrying a large printed manual. The developer, Emergency Medicine Residents' Association, also gives the product a clear professional identity: it is built around emergency-care education rather than general wellness or consumer medication reminders.
I can see particular value during a busy evening when several patients have different suspected sources of infection. A focused guide may reduce the temptation to rely on memory alone, especially for less familiar presentations. It can also help a learner prepare for a discussion with a senior clinician by giving the learner a starting framework instead of an unfiltered list of search results.
The app may be useful in quieter moments too. A resident could use it after a shift to review why a certain antibiotic direction was considered, then compare that reasoning with local teaching. That turns a point-of-care tool into a small study aid. The trade-off is that the learning value depends on active reflection; simply accepting a recommendation without understanding its conditions will not build good prescribing judgment.
It is less compelling for a specialist who already has a preferred, regularly updated institutional reference and needs detailed evidence, extensive dosing nuance, or sophisticated interaction checking. In that situation, a hospital resource, a dedicated pharmacology database, or direct consultation with infectious-disease and pharmacy colleagues may be better. The app’s appeal is speed and focus, not breadth in every direction.
What the rating and version suggest about expectations
The current version is 1.0.1.30, and the app was released on September 22, 2018. I would therefore approach it as a focused reference with a relatively long history rather than assuming it behaves like a modern, constantly expanding clinical platform. A medical app can remain useful over time, but antibiotic practice changes, resistance patterns shift, and institutional policies are not interchangeable.
The 2.4 average rating is a meaningful caution. It does not tell me that the clinical concept is worthless, but it does suggest that the experience may not satisfy everyone who installs it. A reader deciding whether to try it should pay attention to workflow friction, content currency, and whether the guide fits the way their department practices. In clinical software, an app can be conceptually helpful and still be inconvenient enough that staff stop opening it.
I would test it before depending on it in a high-pressure situation. Open it when I have time, learn how its recommendations are organized, and see whether I can reach the relevant section without hesitation. That preparation is especially important for a reference app: discovering its navigation problems for the first time beside an unstable patient is the wrong moment.
The app is free to install, but it includes in-app purchases listed at $9.99 per item. That changes the decision slightly. I would not assume that every part of the experience is available without cost, and I would check what is accessible before making it part of a department-wide workflow. For an individual learner, trying the free portion may be enough to judge whether the organization suits them. For a clinical team, purchasing decisions should also consider whether the content is maintained and whether it aligns with local requirements.
Trade-offs that matter in clinical use
The biggest trade-off is convenience versus context. A concise antibiotic recommendation can save time, but it may not show every factor that influences a real prescription. Local guidelines can differ for legitimate reasons, including resistance data, available formulations, stewardship policies, and specialist preferences. I would never treat a general guide as automatically superior to the protocol governing my workplace.
A second trade-off is speed versus verification. The faster I find an option, the easier it is to overlook a contraindication or a change in the patient’s condition. My safest workflow would be to use the guide after the clinical assessment, then deliberately pause for allergies, organ function, interactions, prior treatment, pregnancy considerations where relevant, and the need for source control. The app can shorten the reference step, but it cannot perform that complete assessment for me.
A third trade-off concerns trust. The developer’s emergency-medicine focus makes the app feel more targeted than a generic medication search, but a professional name should not replace checking the actual recommendation. I would want to know how well the content matches current local practice before relying on it regularly. If a hospital already supplies an approved antimicrobial guide, that resource may deserve priority because it is closer to the prescribing environment in which the decision is being made.
There is also a practical question about paid access. Since individual items cost $9.99, I would compare the purchase against alternatives I already have, including institutional tools and established medical references. The right choice depends on whether the app’s organization saves enough time to justify the added expense. A free download is useful for testing, but it does not automatically mean the complete working experience is free.
Finally, the modest rating means I would keep a backup. That backup could be the department’s official protocol, a trusted clinical database, or a pharmacist’s advice. Having another source is not excessive caution when antibiotic choices affect both the individual patient and broader antimicrobial stewardship.
Who benefits, and who should choose something else?
I think the strongest audience is a medical student, resident, or emergency clinician who wants a specialized ABx reference for quick orientation and already understands that recommendations require interpretation. It can be especially helpful for someone rotating through emergency care and trying to build a repeatable process for infection-related decisions. The app’s narrow focus is an advantage for that user because it avoids turning a time-sensitive question into a general internet search.
It may also help a clinician who learns best from concise decision prompts rather than from a large reference book. Used after a case, it can support a short review: what syndrome did I think was present, what recommendation did the guide suggest, and which patient-specific facts could change it? That reflective use is more valuable than treating the app as a button that produces a final answer.
I would recommend skipping it if you are looking for a patient-facing medication explainer, a complete drug-interaction checker, a diagnostic tool, or a replacement for hospital antimicrobial policy. It is also not the right choice for someone who wants a single source that can be trusted without checking dates, local guidance, and patient-specific risks. In those cases, a broader and actively maintained clinical reference may be a better investment.
For international users, the same caution applies. An emergency-medicine guide can still provide a useful conceptual starting point, but drug availability, resistance, formularies, and prescribing rules vary by location. I would use it to support learning and discussion, then confirm the recommendation against the standards where I practice.
My final take on the guide
The real benefit is not that it makes antibiotic prescribing automatic; it makes the first reference step more focused. That is a worthwhile distinction. When I already have a clinical question and need a compact emergency-oriented reminder, EMRA Antibiotic Guide can be more practical than searching broadly or reaching for a large textbook.
At the same time, the low average rating, the older release history, and the presence of paid items make me cautious about recommending it as the only reference on a shift. I would try the free experience, learn its navigation, and compare its guidance with the protocols I am expected to follow. If it fits that workflow, it could earn a place as a supplementary tool.
My recommendation is therefore selective rather than universal. Medical learners and emergency clinicians who want a focused antibiotic companion should give it a careful trial. Patients, casual users, and professionals needing comprehensive, locally governed prescribing support should choose another resource or use this only alongside one. In my experience, that honest division is where the app makes sense: a quick clinical aid, not a substitute for clinical judgment.
EMRA Antibiotic Guide FAQ
What is the EMRA Antibiotic Guide, and who is it designed for?
The EMRA Antibiotic Guide is a point-of-care clinical reference focused on antimicrobial selection and infectious-disease treatment. It is primarily designed for emergency medicine physicians, residents, medical students, and other healthcare professionals who need concise guidance while evaluating patients. It should be used as an educational and decision-support resource, not as a replacement for clinical judgment, local protocols, laboratory results, or consultation with an infectious-disease specialist.
What information can I find in the EMRA Antibiotic Guide?
The guide generally organizes practical information about commonly encountered infections, recommended antibiotics, dosing considerations, spectrum of activity, allergies, adverse effects, and special patient factors. Its emergency-medicine focus can make it useful when a quick overview is needed during a busy shift. However, users should still verify recommendations against current institutional guidelines, resistance patterns, renal or hepatic function, pregnancy status, and the most recent official prescribing information.
Does the EMRA Antibiotic Guide work offline?
Offline availability depends on the version of the application, the platform, and how its content is delivered after installation. Before relying on it in an emergency department or another location with unreliable connectivity, open the app and test whether the relevant chapters and search features remain accessible without internet access. Updates, account verification, subscription checks, or newly added material may still require a connection, so it is wise to confirm these details before clinical use.
Is the EMRA Antibiotic Guide suitable for patient self-treatment?
No. The EMRA Antibiotic Guide is intended for trained healthcare professionals and learners, rather than for diagnosing infections or choosing antibiotics without medical supervision. Antibiotic selection depends on factors such as the suspected source, severity, cultures, allergies, pregnancy, age, kidney function, drug interactions, and local resistance. Patients should consult a qualified clinician and should never start, stop, or share antibiotics based solely on information found in this app.
Are the recommendations in the EMRA Antibiotic Guide always current and applicable everywhere?
Clinical recommendations can change as new evidence, safety warnings, resistance trends, and stewardship policies emerge. The guide may be highly useful as a concise reference, but its advice may not match every hospital’s formulary or local antibiogram. Before acting on a recommendation, compare it with current institutional protocols, national guidelines, and official drug labeling. Also check the app’s publication date, update history, and any notices explaining revisions or limitations.












